What the anion gap Reflects
The anion gap is a derived value used in laboratory assessment of acid-base balance. It enables clinicians assess whether a patient’s metabolic acidosis is more consistent with an higher burden of unmeasured anions or with a loss of bicarbonate that is matched by a rise in chloride. In simple terms, the anion gap is a valuable clinical aid for identifying patterns in electrolyte balance and guiding the next step in the diagnostic approach.
Most versions of the calculation use serum sodium, serum chloride, and serum bicarbonate. The traditional anion gap formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This simple formula provides a calculated value that reflects the relationship among major measured electrolytes. Because sodium is the dominant measured cation and chloride plus bicarbonate account for much of the measured anion content, the result gives a useful snapshot of acid-base analysis. When the result is outside the expected reference range, it can point toward a specific metabolic disturbance.
The anion gap does not identify a single disease. Instead, it supports clinical interpretation by focusing the differential diagnosis. A high gap suggests the presence of unmeasured acids or toxins, while a normal gap often indicates bicarbonate loss with compensatory chloride retention. That distinction is essential to acidosis workup.
How to Operate an Anion Gap Calculator
This Anion Gap Calculator serves as a simple way to use the anion gap formula using current serum electrolytes. For correct use, input the patient’s laboratory values for Na, chloride, and bicarbonate. The calculator then produces the calculated value, which can be compared with the expected reference range and interpreted in the context of the patient’s acid-base status.
The process is straightforward:
- Check the most recent serum sodium, serum chloride, and serum bicarbonate values. Type those numbers into the Anion Gap Calculator. Check the calculated value and compare it with the local reference range. Determine whether albumin is low, since that can change the corrected value. Review the result alongside symptoms, history, and other diagnostic data.
Using this tool is not just about obtaining a number. It is about integrating that number into a broader clinical framework. A mild elevation may be significant in one patient and less important in another, depending on the underlying cause and the presence of a mixed process. Because acid-base disorders are often dynamic, repeat testing may be needed when the clinical picture changes.
It is also important to remember that a calculator is a supportive tool, not a standalone diagnosis. For example, a patient with low bicarbonate may have either high anion gap metabolic acidosis or normal anion gap metabolic acidosis. The calculator helps separate those possibilities and shows which branch of the differential diagnosis should be pursued first.
Interpreting High Anion Gap
A high-gap metabolic acidosis means that unmeasured anions are accumulating in the bloodstream. This often reflects the addition of acids that are not directly captured by routine serum chemistry. The result is a larger gap between measured cations and measured anions, usually alongside a reduced serum bicarbonate.
Common causes include lactic acidosis, ketoacidosis, and toxic ingestion. These are among the most important diagnoses to consider because they can worsen rapidly and may require urgent treatment. The anion gap is therefore a important clue in identifying an underlying cause of metabolic acidosis.
Lactic acidosis occurs when lactate accumulates, often due to hypoperfusion, sepsis, hypoxia, seizures, or certain medications and toxins. In this setting, the elevated gap reflects excess acid production or impaired clearance. Clinical context is essential, because the same laboratory pattern can occur in a wide range of critical conditions.
Ketoacidosis is another classic reason for an elevated gap. It may occur in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation states. In these cases, ketone bodies function as unmeasured anions, raising the gap while bicarbonate falls. Blood glucose, ketones, and the overall clinical picture help distinguish these scenarios.
Toxic alcohol ingestion is a major diagnostic concern when the gap is elevated without an obvious explanation. Substances such as methanol, ethylene glycol, and related compounds can produce a high anion gap metabolic acidosis and may also create an elevated osmolar gap early in the course. Because timing matters, a normal osmolar gap does not completely exclude toxic exposure. If suspicion is high, urgent evaluation and targeted testing are warranted.
In practice, the elevated gap should trigger a structured diagnostic approach. Consider the patient’s symptoms, exposure history, medication list, vital signs, and organ function. An arterial blood gas can help confirm the severity of the acid-base disorder and identify whether ventilation is compensating appropriately. Together, these data sharpen the differential diagnosis and help prioritize treatment.
Explaining a Typical Anion Gap
A normal-gap metabolic acidosis is typically caused by bicarbonate loss that is countered by a rise in chloride, which is why it is often called chloride-associated acidosis. In this pattern, the body depletes base rather than building up unmeasured acid. The anion gap is kept within the reference range even though the patient is acidemic.
One of the principal causes is diarrhea, which results in gastrointestinal bicarbonate loss. Because the body seeks to maintain electroneutrality, chloride rises as bicarbonate falls. This can lead to a marked metabolic acidosis without an elevated anion gap.
Another major cause is renal tubular acidosis, a group of disorders in which the kidneys do not effectively acidify urine or conserve bicarbonate. Depending on the subtype, the patient may show persistent acidemia, low bicarbonate, and a normal anion gap. Renal function tests, urine studies, and the broader clinical context help separate this from gastrointestinal losses.
Other causes of normal gap acidosis may include certain medications, early kidney disease, or iatrogenic chloride load from intravenous fluids. The key point is that a normal result does not eliminate clinically important acidosis. Instead, it focuses on processes that cause bicarbonate loss or impaired renal acid handling.
Because the pattern can be subtle, careful acid-base analysis is useful. If the clinical picture seems more severe than the calculated value suggests, consider whether a mixed acid-base disorder is present or whether the reference range used by the laboratory is different from the one assumed by the calculator.
Correcting the Anion Gap for Albumin
Albumin is a key not directly measured anion in plasma, so reduced albumin can make the measured anion gap seem lower than it really is. This is why clinicians often estimate a corrected anion gap when hypoalbuminemia is present. Without this adjustment, a clinically important high-gap process may be missed.
The concept is easy: if albumin is reduced, the “missing” negative charge is not part of the measured chemistry panel. As a result, the gap may look deceptively normal. The corrected value better reflects the patient’s true acid-base status and enhances clinical interpretation.
Correcting the anion gap is especially helpful in hospitalized or critically ill patients, where low albumin is frequent. In those settings, relying only on the raw value may downplay the severity of an acid-base disorder. The corrected value can reveal an elevated gap that supports an underlying high-gap process such as lactic acidosis, ketoacidosis, or toxic alcohol ingestion.
This adjustment is one reason the anion gap should be viewed as part of a broader set of acid-base disorders rather than as a standalone number. Albumin levels, serum chemistry, and arterial blood gas data all work together to a more accurate interpretation guide. When the corrected anion gap differs significantly from the uncorrected result, that discrepancy itself is an meaningful clue.
Diagnostic Framework for Acidosis
When evaluating metabolic acidosis, the anion gap is a helpful first step for the differential diagnosis. A systematic approach helps progress from the calculated value to the probable underlying cause.
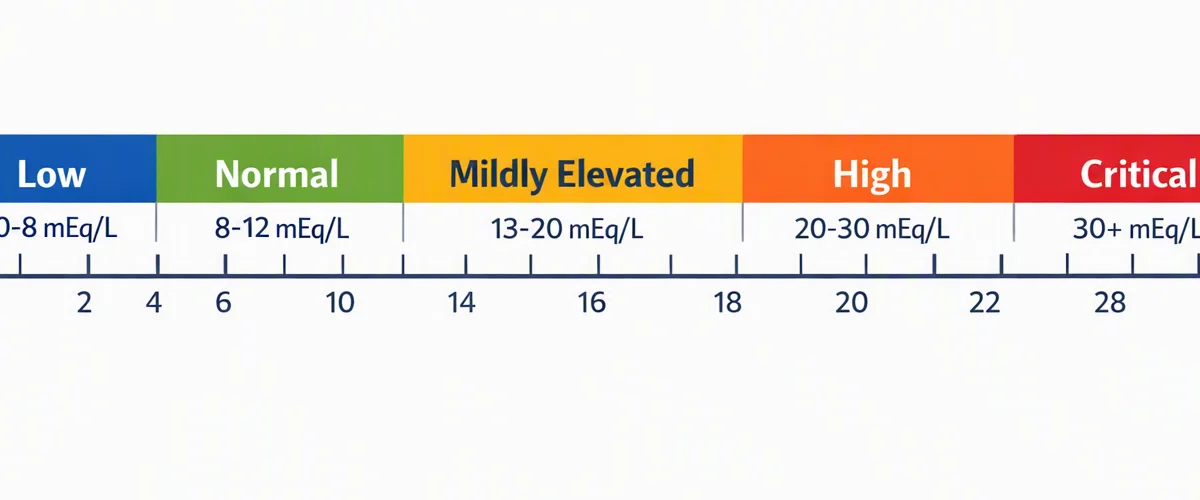
To begin, confirm that the patient truly has acidosis with an arterial blood gas if needed. This helps distinguish metabolic acidosis from respiratory disorders and identifies compensation. Then examine the anion gap, serum bicarbonate, and chloride pattern to decide whether the acidosis is high-gap or normal-gap.
For an elevated gap, evaluate accumulation of organic acids, lactate, ketones, or toxins. For a normal gap, think about gastrointestinal bicarbonate loss, renal tubular acidification defects, or chloride-rich fluid administration. In many cases, the next step is focused testing based on the leading branch of the differential diagnosis.
An osmolar gap can be a useful adjunct when toxic alcohol https://anion-gap-values042.cloudhinter.com/posts/can-low-albumin-lead-to-a-low-anion-gap ingestion is possible. If the osmolar gap is elevated, it may support suspicion for methanol, ethylene glycol, or another osmotically active substance. However, the osmolar gap and anion gap are adjunctive, not interchangeable. A patient may have one abnormality, both abnormalities, or neither depending on timing and metabolism.
Clinical assessment should also account for the trajectory of illness. A rapidly rising gap can suggest evolving critical illness, while a stable normal gap may point to chronic renal tubular acidosis or ongoing diarrhea. The optimal diagnostic approach combines the calculated value with history, exam findings, and repeated laboratory assessment when needed.
Typical Pitfalls and Limitations
While useful, the anion gap has constraints. A typical pitfall is lab error, which can occur from collection problems, transcription issues, or analyzer variation. If the result does not fit the patient’s clinical picture, retesting may be required before reaching conclusions.
The reference range can also differ by lab technique. A result that appears unexpected in one system may be borderline or even within range in another. For that reason, interpretation should be tied to the specific lab’s interval rather than a broad threshold.
Another limitation is the possibility of a mixed acid-base disorder. A patient may have both high anion gap metabolic acidosis and metabolic alkalosis, or a increased-gap process plus a usual-gap process at the same time. In such cases, the measured value may mask the full degree of the metabolic disturbance.
The clinical picture matters more than any isolated result. For example, a patient with serious disease, altered mental status, or shock may need immediate evaluation even if the anion gap is only mildly shifted. Likewise, a patient with hypoalbuminemia may require a calculated correction before the laboratory data can be understood correctly.
When You Should Seek Prompt Medical Evaluation
Severe acidosis can be fatal, especially when it occurs with severe disease. Rapid breathing, disorientation, listlessness, chest pain, persistent vomiting, hypotension, or signs of dehydration may indicate a serious disorder requiring immediate care. The presence of any concerning signs should prompt immediate clinical evaluation.
Prompt evaluation is particularly important when a high anion gap acidosis is suspected from elevated lactate, ketoacidosis, or toxic alcohol ingestion. These problems may worsen quickly and can lead to organ dysfunction if not recognized early. A clinician may order repeat blood chemistry, an arterial blood gas, lactate, ketones, renal studies, or toxin testing depending on the presentation.
Get immediate medical help if the patient is confused, difficult to arouse, breathing rapidly, or showing signs of shock. The anion gap calculator is a helpful screening tool, but it cannot replace emergency evaluation when the patient appears unstable.
FAQ
What does the anion gap mean and why does it matter in acidosis?
The anion gap is a derived number from routine serum chemistry that helps identify metabolic acidosis. It is important because it separates high anion gap metabolic acidosis from normal anion gap metabolic acidosis and guides the differential diagnosis by pointing toward the underlying cause.
How do you calculate the anion gap using sodium, chloride, and bicarbonate?
The most common anion gap calculation is serum sodium minus the sum of serum chloride and serum bicarbonate. In formula form, it is: anion gap = sodium − (chloride + bicarbonate). An Anion Gap Calculator performs this calculation automatically from the laboratory values.
What are the causes of high anion gap metabolic acidosis?
Frequent causes include lactic acidosis, ketoacidosis, and toxic alcohol ingestion. Other causes may include kidney failure, certain medications, and toxin exposure. The elevated gap reflects unmeasured acids accumulating in the blood.
What leads to a normal anion gap metabolic acidosis?
Normal anion gap metabolic acidosis is often caused by loose stools, RTA, and chloride-heavy fluid therapy. It is also called a hyperchloremic state because chloride rises as bicarbonate decreases, keeping the gap within the reference range.
Why should the anion gap corrected for albumin?
Albumin is a major unmeasured anion, so low albumin can make the anion gap look spuriously normal. Correcting for hypoalbuminemia provides a corrected anion gap that more accurately reflects the true acid-base disorder and can identify a hidden high-gap process.