What Is the Anion Gap?
The anion gap is a calculated measurement used to check electrolytes in the system and to assist with evaluation of an acid-base disorder. It is not a directly recorded lab finding. Instead, it is worked out from common blood chemistry values, usually including sodium, chloride, and bicarbonate. In some settings, potassium may also be included in the formula.
Clinicians use the anion gap to look for a underlying metabolic disturbance, especially when there is worry for metabolic acidosis. A above-normal value can suggest extra unmeasured acids in the blood, while a reduced value can indicate issues such as low serum albumin or laboratory differences. Because the calculation depends on routine serum electrolytes, it is often part of the larger medical assessment of a patient with abnormal blood chemistry.
In basic terms, the anion gap helps clinicians interpret how positively and negatively charged particles in the blood are offsetting each other. That balance is part of normal acid-base balance, and a change can be an useful clue when reviewing laboratory results.
How an Anion Gap Calculator Works
An Anion Gap Calculator is a tool that uses lab values from a chemistry panel to determine the anion gap promptly and reliably. The calculator generally takes the measured concentrations of sodium, chloride, and bicarbonate, and in some versions also includes potassium. It then follows the standard anion gap calculation formula to produce a numerical result.
For example, a typical formula is:
Anion gap = sodium - (chloride + bicarbonate)
When potassium is included, the formula may be adjusted slightly. Because the calculation is based on lab values, the result depends on the quality of the sample and the accuracy of the testing method. That is why the calculator is best used as part of broader clinical interpretation, not as a stand-alone diagnosis.
An Anion Gap Calculator is especially useful when reviewing a possible electrolyte imbalance or acid-base disorder. It can help identify a high anion gap or low anion gap pattern that deserves closer attention. In pediatric care, the calculator should be paired with the child’s age, symptoms, and other blood chemistry findings to support a more accurate conclusion.
Do Children Have Varying Anion Gap Ranges Than Adults?
Yes, pediatric patients can have varying ranges for the anion gap versus adults. The notion of a normal range is not always the same across every age, because children are not simply miniature adults. Maturation, metabolism, and hydration status change over time, so the relevant reference range may differ by age and by laboratory.
In practice, clinicians often consider age-based reference ranges or a children’s reference interval when reviewing results in young patients and adolescents. Some laboratories use a mildly different reference interval for pediatric patients, while others apply the same overall interval across age groups but urge careful interpretation in interpretation. This is why the same number may be viewed differently depending on the patient’s age and the local lab method.
The key point is that the anion gap should not be interpreted in isolation. A result that seems abnormal by adult standards may still match the child’s clinical picture, especially if the rest of the evaluation is reassuring. Conversely, a value within the expected range does not always exclude a significant problem if symptoms and other tests point to otherwise.
Why Anion Gap Values Can Vary in Pediatrics
Several factors can influence the anion gap in pediatric patients. One major factor is albumin, a negatively charged protein in the blood. Because albumin contributes to the overall charge balance, lower levels can reduce the measured gap. This is why hypoalbuminemia can lead to a deceptively low result even when another disorder is present.
Growth-related changes also matter. As babies, children, and teens develop, their fluid status, kidney handling of acids and bases, and metabolism can change. These shifts alter acid-base balance and may influence how a result should be read during clinical interpretation. A child with growth spurts, dehydration, or sudden illness may have different laboratory results than a stable outpatient.
Testing methodology is another important reason values vary. Different analyzers, calibration approaches, specimen handling practices, and reporting conventions can produce different results for the same sample. As a result a reported normal range may differ from one institution to another. When interpreting an anion gap, clinicians should always compare the result to the lab’s stated reference range rather than assuming a universal value.
In addition, serum albumin concentration, the presence of other unmeasured ions, and overall serum electrolytes can influence the final number. For children, these factors make context especially important during medical assessment.
Common Causes of an Abnormal Anion Gap in Children
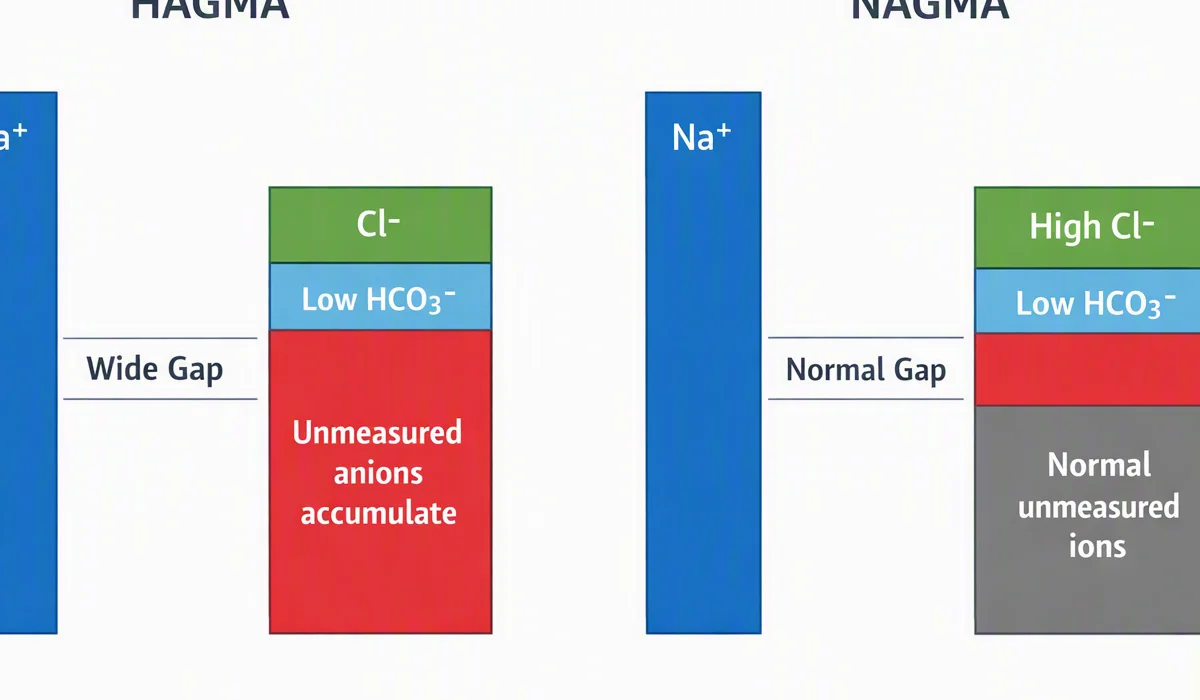
An abnormal anion gap in children frequently indicates an underlying metabolic acidosis or a different metabolic issue that needs evaluation. A high anion gap usually points to the buildup of acids that are not directly measured on the electrolyte panel. Common causes include lactic acidosis, ketoacidosis, and renal disease.
Lactic acidosis can occur when tissues are not receiving enough oxygen or when the body is under significant stress from infection, poor circulation, or severe illness. In this setting, lactic acid builds up and changes the acid-base balance. Ketoacidosis may occur when the body breaks down fat rapidly for energy, leading to the accumulation of ketones. This can be seen in diabetes and sometimes in fasting or other metabolic conditions.
Renal disease can also cause a high anion gap because the kidneys are less able to eliminate acid effectively. When acid builds up, the blood chemistry changes, and the gap may rise. In pediatric care, these causes are evaluated alongside hydration status, glucose, kidney function, and symptoms.
A low anion gap is less common but may occur with hypoalbuminemia, measurement variation, or unusual electrolyte patterns. Because both high anion gap and low anion gap patterns can reflect important disease processes, pediatric interpretation should be careful and systematic.
How to Read an Anion Gap Result in a Child
Proper interpretation of the anion gap in a child requires the clinical picture. The number alone does not diagnose a condition. Instead, healthcare providers consider the full picture, including symptoms, the electrolyte panel, a blood gas test, and the child’s pH. These findings help determine whether there is a true acid-base disorder and how severe it may be.
For instance, a child with throwing up, belly pain, and high glucose may need evaluation for ketoacidosis. A child with a fever, hypotension, and poor circulation may need assessment for lactic acidosis. A child with renal issues may have impaired acid removal from renal disease. In every case, the anion gap is one piece of the diagnostic process.
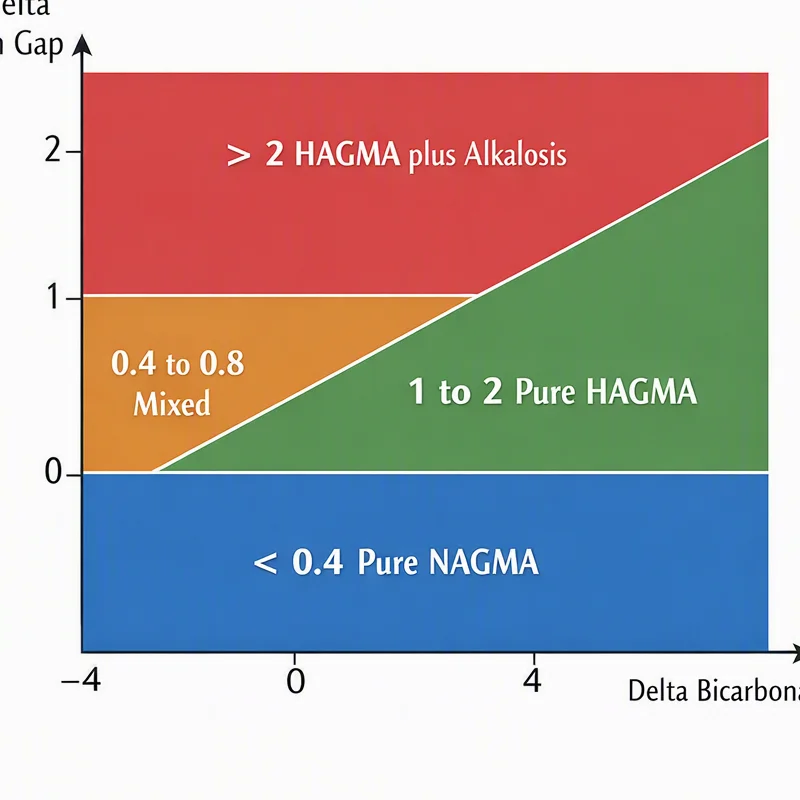
It is also helpful to compare the result with bicarb, pH, and any existing blood gas values. A reduced bicarbonate level with a elevated gap suggests metabolic acidosis, but the full pattern is more important above any single result. The goal is medical evaluation rather than single number reading.
When you use the Anion Gap Calculator, clinicians should check the measurements, review the listed lab values, and assess whether the result aligns with the rest of the child’s clinical picture. This matters especially in children’s health, where symptoms can shift rapidly.
When a Increased or Low Anion Gap Needs Follow-Up
An outside-the-normal-range result may need more evaluation depending on the child’s symptoms and overall condition. A increased anion gap along with fever, changes in breathing, altered mental status, or signs of poor perfusion can suggest a serious metabolic problem that needs prompt evaluation. A low value may also need follow-up if it is unanticipated, persistent, or paired with worrisome findings.
Dehydration can affect blood chemistry and may worsen an acid-base disturbance. In some children, dehydration comes with vomiting, diarrhea, fever, or poor intake and can contribute to abnormal lab patterns. If the child also has hypoalbuminemia, the gap may appear reduced than expected, which can make interpretation more difficult.
Toxic ingestion is another reason an abnormal gap may need urgent attention. Certain ingestions can produce a high gap metabolic acidosis, and the child may need urgent testing and treatment. In these situations, the anion gap is often only one clue among many and should be interpreted with history, exam, and additional laboratory tests.
Follow-up is especially important when the result does not fit the clinical https://anion-gap-reference119.brightsora.com/posts/anion-gap-calculator-derived-from-bmp-values picture, when symptoms are worsening, or when there is concern for a serious underlying illness. The more abnormal the value, the more strongly clinicians should consider a full clinical assessment.
Limitations of the Anion Gap in Pediatric Testing
Although useful, the anion gap has significant limitations. One key limitation is the normal range itself. Because the reference range may differ by lab and age group, a value should always be interpreted according to the testing facility’s standards. This is especially relevant in pediatrics, where the same number may not carry the same meaning across all settings.
Analytical error can also affect the result. Minor changes in sodium, chloride, or bicarbonate can change the calculated gap. Since the anion gap formula depends on these measured values, any inaccuracy in the underlying electrolyte data can alter the final number. Specimen handling, analyzer calibration, and reporting practices all play a role in testing methodology.
Another important limitation is that a normal gap does not rule out disease. Some conditions may not produce a clearly elevated gap early on, and mixed disorders can mask one another. Likewise, a low result may be driven by low albumin rather than a primary metabolic problem. This is why clinicians use the anion gap as part of a broader diagnostic approach rather than as a single decisive marker.
In short, the anion gap is a valuable tool, but it has diagnostic limitations. The best use of an Anion Gap Calculator is to support thoughtful interpretation of pediatric laboratory data, not to replace clinical judgment.
FAQ: Pediatric Anion Gap Questions
Can pediatric patients have different anion gap ranges than adults?
Yes, they can. Children can have different expected values depending on age, the laboratory’s normal range, and the testing method used. Pediatric patients and teens should be interpreted using age-aware medical interpretation when available, rather than assuming adult expected values always apply.
What is a normal anion gap interval in children?
The reference range can differ by lab and by age range, so there is not one universal number for all children. It is best to use the local normal interval provided with the test results. A clinician may also use a child reference range when assessing the result in the context of the child’s age and condition.
Why might a child have a raised anion gap?
A child may have a raised anion gap because of metabolic acidosis from causes such as lactic acidosis, ketone-related acidosis, or kidney disease. Other serious illnesses can also affect the gap. The result should be considered alongside symptoms, blood gas findings, and the rest of the electrolyte panel.

Can low albumin affect the anion gap in pediatrics?
Yes. Albumin is an important contributor to the blood’s charge balance, so low albumin can lower the measured anion gap. This may make the result look less abnormal than it really is. In pediatric care, low albumin should be considered during pediatric review of the lab result.
When should an abnormal anion gap in a child be evaluated further?
An abnormal result should be evaluated further when it is paired with symptoms, a concerning blood gas result, abnormal pH, signs of illness, or suspicion for a serious metabolic problem. Prompt evaluation may be needed for dehydration, toxic ingestion, severe acidosis, or other unstable findings. A full clinical evaluation helps determine whether the lab pattern reflects a true medical problem.