What’s the Anion Gap?
The anion gap is a derived result used in acid-base interpretation to spot alterations in electrolytes that may point to an underlying acid-base issue. It contrasts the major measured positive ions and negative ions in the blood, mainly sodium and chloride, along with serum bicarbonate in the formula. Although it is not a direct measurement of a single substance, it offers a useful picture of electrolyte balance and overall serum chemistry.
Clinically, the anion gap helps uncover the presence of unmeasured anions or an anion deficit that may not be obvious from routine laboratory values. Because the blood must stay electrically neutral, any gap between measured cations and anions hints that other ions are present but not directly listed on a standard electrolyte panel. That is why the anion gap is such a useful diagnostic aid in evaluating acid-base problems.
How the Anion Gap Matters in Acid-Base Interpretation
The anion gap is important because it helps differentiate metabolic acidosis into types that guide the differential diagnosis. In many cases, the first question is whether the patient has a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis. This difference alters the clinical interpretation, next steps, and urgency of care.
In acid-base balance, the body relies on a tightly regulated buffer system involving bicarbonate, lungs, and kidneys. When acid builds up or bicarbonate is lost, the acid-base balance shifts. The anion gap helps determine whether that shift is due to increase of acids that create unmeasured anions or due to direct bicarbonate loss with compensatory chloride retention.
In practice, the anion gap is part of broader clinical interpretation. It should not be used alone. Instead, it is interpreted with symptoms, blood gas data, the electrolyte panel, and the overall clinical picture. That combined approach helps reduce missed diagnoses and improves the accuracy of acid-base interpretation.
How an Anion Gap Calculator Functions
An anion gap calculator is a basic utility that uses a standard formula to estimate the gap from common laboratory values. Most calculators need serum sodium, serum chloride, and serum bicarbonate. Some versions also add albumin so they can provide a corrected anion gap.
The underlying logic is clear: sodium is the main measured cation, while chloride and bicarbonate serve as major measured anions. The calculator compares these values to estimate the amount of unmeasured ions in the blood. This makes it a rapid diagnostic aid when assessing a patient’s electrolyte panel or serum chemistry.
Using an anion gap calculator can help clinicians and learners quickly identify whether the result points to a metabolic problem. It is especially helpful when evaluating metabolic acidosis, because the gap may point toward lactate, ketones, toxins, or kidney-related acid retention. The calculator does not replace judgment, but it makes interpretation more streamlined.
Anion Gap Formula and Normal Ranges
The most common anion gap formula can be written as:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
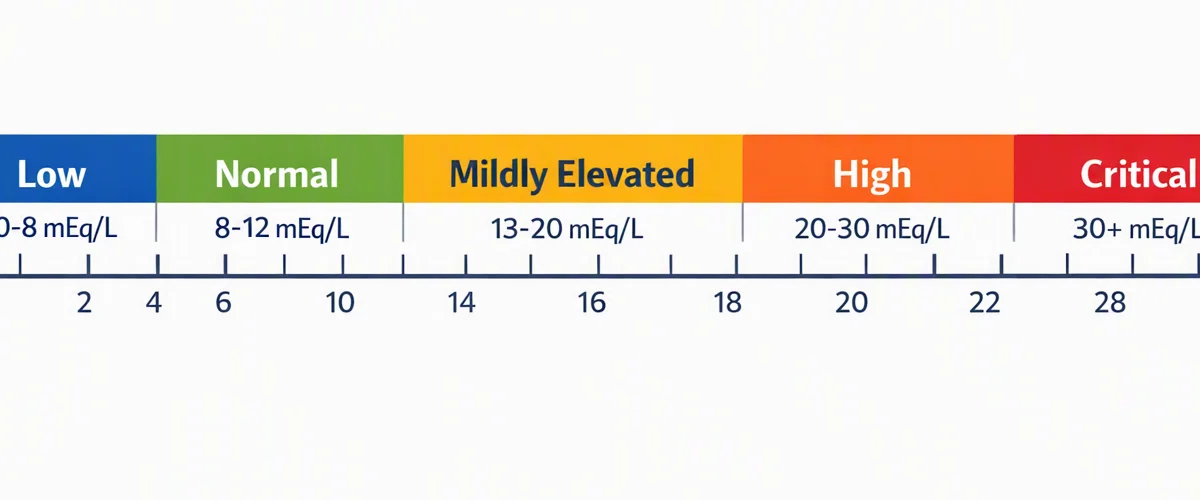
Some testing facilities apply slightly different equations or reference methods, but the concept is identical. The result is then measured against the lab’s reference range. A usual normal anion gap is often around 8 to 12 mEq/L, though the exact range depends on the laboratory and measurement method.
Because the normal range can vary, it is important to interpret the number using the local reference range rather than a single universal cutoff. The presence of albumin also influences the expected result. Since albumin is a negatively charged protein, lower levels can make the anion gap appear falsely low unless an albumin adjustment is made.
In other words, a “normal” result is not always truly normal. Understanding the formula, the lab’s reference range, and the effect of albumin can make the calculation more accurate and clinically useful.
How to Read a Increased Anion Gap
A elevated anion gap metabolic acidosis implies that acids are accumulating in the body and resulting in unmeasured anions. This is usually the first clue to severe illness. Common causes include lactic acidosis, ketoacidosis, renal failure, and some poisonings.
Lactic acidosis develops when lactate builds up due to inadequate circulation, shock, severe infection, seizures, or other conditions that limit oxygen delivery or utilization. Ketoacidosis may develop in diabetes, starvation, or alcohol-related states, where ketones become the primary acids. In both settings, the body’s buffer system is overrun, and the anion gap rises.
Renal failure can also cause a high gap because the kidneys cannot excrete acid efficiently, resulting in retention of acids and unmeasured anions. This makes kidney function an important part of the differential diagnosis.
When the anion gap is elevated, the interpretation should center on the likely source of acid production or impaired clearance. The calculator can suggest the problem, but the cause still needs clinical correlation with history, medications, symptoms, and lab testing.
How to Read a Standard Anion Gap
A normal anion gap metabolic acidosis usually means the body is losing bicarbonate or retaining chloride, rather than building up a large amount of unmeasured acid. In this context, the total gap stays close to the reference range even though the patient still has a important acid-base disorder.
Common causes include bicarbonate loss from diarrhea and abnormal renal acid handling from renal tubular acidosis. These conditions often lead to a hyperchloremic pattern, where the chloride level rises as bicarbonate falls. That pattern keeps the anion gap fairly stable while the bicarbonate level declines.
Recognizing this pattern matters because a normal anion gap does not rule out serious disease. A patient with severe diarrhea or renal tubular acidosis can still be markedly acidotic. In these cases, the anion gap calculator supports the broader clinical interpretation by showing that the acid-base disorder is present even if the gap is not elevated.
Albumin Compensation and How It Affects the Result
Albumin is one of the main unmeasured anions in the blood. When hypoalbuminemia is present, the calculated anion gap may be reduced than expected because there are less negatively charged proteins contributing to the gap. That is why albumin compensation is so useful.
A corrected anion gap modifies the result to account for the patient’s albumin level. This helps avoid missing a true high-gap disorder in someone with low protein levels. In clinical terms, the correction improves interpretation and reduces false reassurance.
Albumin adjustment is especially helpful in hospitalized patients, those with chronic illness, malnutrition, liver disease, or inflammatory conditions. In these settings, low albumin can obscure a clinically important increase in the gap. Using a corrected value improves the accuracy of acid-base analysis and helps reveal whether hidden acids are present.
Because albumin is a major blood protein in serum, even moderate changes can affect the result. A calculator that includes albumin compensation is often more helpful than a basic formula alone.
Typical Causes of Anion Gap Abnormalities
Several conditions can shift the anion gap, and a thorough differential diagnosis is important. Causes of high-gap acidosis often include toxins, uremia, and marked metabolic stress. Other common examples include salicylates and ethylene glycol.
Uremia from advanced kidney dysfunction can raise retained acids and widen the gap. Salicylates may create a complex acid-base picture, sometimes with a mixed disorder, so the anion gap is only one part of the assessment. Ethylene glycol exposure is a toxic ingestion that can result in severe high-gap acidosis, often with additional clues on blood testing and clinical history.
Low or normal gap abnormalities are also important. These often suggest bicarbonate loss, chloride gain, or albumin changes rather than an accumulation of classic organic acids. The key is not only to calculate the number but also to relate it to the patient’s presentation, medication list, renal function, and possible toxic ingestion.
Detailed Example Calculations
This is a simple worked example using common lab values:
- Sodium: 140 Chloride: 102 Bicarbonate: 24
Using the formula:
Anion gap = 140 - (102 + 24) = 14
If the lab’s reference range is 8 to 12, this result is modestly increased. Depending on the clinical context, the patient may need further evaluation for early high-gap metabolic acidosis, mild ketosis, lactate elevation, or another cause of increased unmeasured anions.
Now consider a second example:
- Sodium: 138 Chloride: 110 Bicarbonate: 18
Anion gap = 138 - (110 + 18) = 10
This result is within a typical reference range, but the low bicarbonate indicates acidosis. That pattern suggests normal anion gap metabolic acidosis, which should prompt evaluation for diarrhea, renal tubular acidosis, or other sources of bicarbonate loss.
These examples show how a calculator can support interpretation by linking serum sodium, serum chloride, and serum bicarbonate to the overall clinical picture.
Limitations and Common Mistakes
Even a reliable anion gap calculator has limitations. One common mistake is assuming the result alone establishes a diagnosis. The gap is an indicator, not a final answer. A second issue is laboratory error, which can affect the calculation if one of the input values is inaccurate.
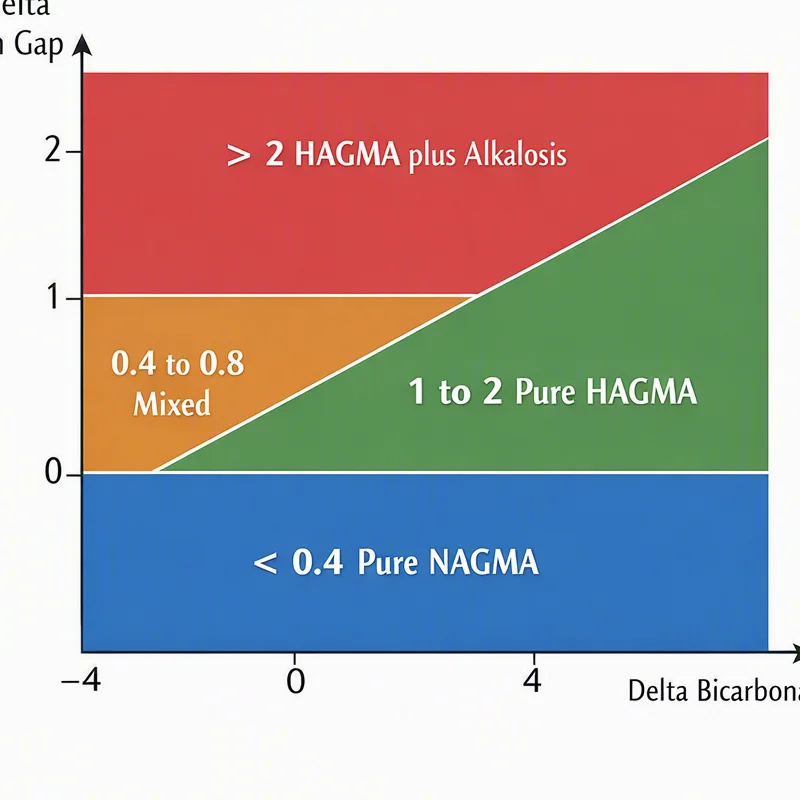
Another significant mistake is missing a mixed acid-base disorder. For example, a patient can have a high-gap acidosis and a concurrent metabolic alkalosis or respiratory disorder that makes the numbers harder to interpret. In these situations, reliance on the calculator alone can lead to misclassification.
Albumin effects are also frequently overlooked. Without albumin correction, a clinically important high-gap disorder may be missed in a patient with hypoalbuminemia. In short, the calculator is most helpful when combined with clinical context, a blood gas, and careful review of the full chemistry panel.
When to Seek Clinical Evaluation
An abnormal gap should be interpreted alongside the patient’s symptoms and overall condition. Signs such as rapid breathing, confusion, vomiting, dehydration, severe weakness, chest discomfort, or altered mental status may require prompt evaluation. A blood gas can help clarify the severity of the acid-base problem and show whether compensation is present.
Additional concern is warranted when there are significant electrolyte abnormalities, suspected toxic ingestion, worsening kidney function, or evidence of severe acidosis. Because metabolic acidosis can advance fast, some patients need urgent care rather than routine follow-up.
If an abnormal result appears with concerning symptoms, the anion gap calculator should be treated as a starting point, not the endpoint. The next step is a full clinical evaluation that may include repeat labs, toxicology testing, renal studies, and a more detailed acid-base assessment.
Frequently Asked Questions
What does an anion gap calculator show?
An anion gap calculator calculates the variation between measured cations and measured anions in the blood. It uses serum sodium, serum chloride, and serum bicarbonate to detect unmeasured anions and aid acid-base interpretation. It is a useful diagnostic aid for detecting metabolic acidosis and related disorders.
What is normal anion gap range?
A common reference range is usually about 8 to 12 mEq/L, but the exact normal anion gap depends on the laboratory and method used. Always interpret the result using the local lab’s reference values and consider whether albumin may be lowering the apparent gap.
How do you correct the anion gap for albumin?
Albumin correction modifies the result upward when hypoalbuminemia is present, because low albumin can hide a true elevation. https://anion-gap-guide100.trexgame.net/anion-gap-calculator-for-kidney-failure-understanding-the-results The exact formula may vary, but the goal is the same: to obtain a more accurate corrected anion gap that reflects the patient’s true acid-base status.
What causes a high anion gap metabolic acidosis?
Common causes include lactic acidosis, ketoacidosis, renal failure, uremia, and toxic ingestions such as salicylate poisoning and ethylene glycol poisoning. These conditions raise acids or unmeasured ions, leading to a high anion gap metabolic acidosis.
Can a normal anion gap still indicate a serious acid-base disorder?
Absolutely. A normal anion gap metabolic acidosis can still be medically important and may occur with diarrhea or renal tubular acidosis. The gap may stay normal because the problem is usually bicarbonate loss rather than accumulation of new acids, so the blood still shows a meaningful acid-base disorder.