What the Anion Gap Measures
The anion gap is a practical way to look at acid-base balance through routine blood chemistry. It assists estimate the relationship between positively charged ions and negatively charged ions in the blood, notably when reviewing serum sodium, serum chloride, and serum bicarbonate. Because many important ions are not directly measured on a standard panel, the anion gap acts as a useful window into unmeasured anions and, indirectly, unmeasured cations.
In plain terms, the anion gap reflects electroneutrality, the principle that blood must remain electrically balanced. When the measured values from a basic metabolic panel are compared, the result can signal whether there is an acid-base disorder such as metabolic acidosis. That is why the anion gap is such a important diagnostic tool in everyday lab interpretation.
The calculation does not identify a disease by itself. Instead it helps guide the differential diagnosis and place a laboratory result into clinical context. A normal value can be encouraging, but it does not always exclude a serious problem. Likewise, an abnormal value should be interpreted with the rest of the serum electrolytes, the patient’s symptoms, and any relevant history of illness or medication exposure.
How an Anion Gap Calculator Functions
An anion gap calculator applies a basic formula to the numbers in a standard electrolyte panel. The usual version uses sodium, chloride, and bicarbonate to estimate the gap between measured cations and anions. Because these are standard components of a basic metabolic panel, the calculation is simple to perform and often is displayed automatically in laboratory results.
Although the exact formula can differ by laboratory, the classic approach is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some labs use slightly different methods or include potassium in special cases, but the core idea remains the same. The calculator is not measuring a single substance. Instead, it is a mathematical shortcut that estimates how much “gap” exists after the measured serum electrolytes are included. That gap reflects the presence of acids, proteins, or other ions not directly captured by routine testing.
Used well, the calculator supports a wider diagnostic evaluation. It helps clinicians determine whether the pattern looks like high anion gap metabolic acidosis, a normal anion gap process, or a low anion gap pattern that may suggest another issue. The value should not ever be interpreted in isolation; it is one part of a larger blood chemistry assessment.
Standard Range and Expected Values
The usual anion gap is not consistent across each lab. One reference range may vary depending on the analyzer, calibration method, and whether potassium is included. This is why laboratory variation is so important in lab interpretation. A result that looks slightly high in one setting may still fit inside expected limits in another.
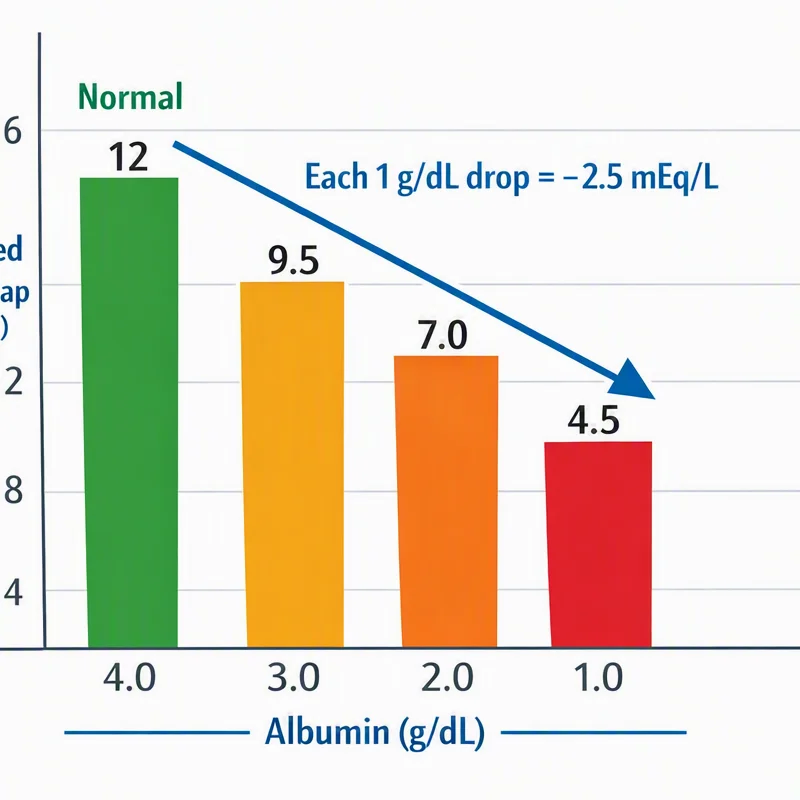
Albumin also influences the expected range. Since albumin is a negatively charged protein, lower levels can decrease the measured anion gap even when the underlying acid-base state is abnormal. For that reason, a “normal” result can sometimes be unreliable if hypoalbuminemia is present.
As a practical rule, check the result with the specific lab’s printed reference interval rather than basing it on a single universal number. Note whether the test was drawn as part of a basic metabolic panel or a broader electrolyte panel, and review whether other values suggest an electrolyte imbalance or a broader metabolic disturbance. The reference range is a reference, not an endpoint.
Reading High Anion Gap
A raised anion gap metabolic acidosis generally suggests acid levels are increased in the bloodstream or a rise of unmeasured anions. This result should be taken seriously because it may signal an serious acidotic state. The result often appears alongside low bicarbonate and may be accompanied by clinical findings such as rapid breathing, confusion, nausea, or weakness.
Typical causes include lactic acid buildup, ketoacidosis, renal insufficiency, uremic state, toxic alcohol ingestion, and salicylate toxicity. Each cause has its own clinical pattern. For example, lactic acidosis can occur with tissue hypoperfusion or severe infection, while ketoacidosis is often associated with insulin deficiency or prolonged fasting. Toxic exposures should be considered when the presentation is sudden, severe, or unexplained.
In practice, a high result from an anion gap calculator should prompt evaluation of the underlying cause rather than a focus on the number alone. Review the full overall context, including medications, kidney function, glucose, lactate, and ketone status. If the elevation is marked, the pattern may represent a significant acid-base imbalance that requires prompt attention.
Interpreting a Normal or Decreased Anion Gap
A normal anion gap metabolic acidosis can arise when bicarbonate is lost but the gap does not change because chloride rises to compensate. This pattern is sometimes called hyperchloremic metabolic acidosis. It often points toward gastrointestinal bicarbonate loss, certain kidney problems, or other causes of non-gap acidosis. The key is to recognize that a normal gap does not mean no acidosis is present.
A low anion gap is less common and is often overlooked. One of the most frequent explanations is decreased albumin, because reduced albumin lowers the expected gap. Another important consideration is myeloma, where abnormal proteins can alter the balance of charged particles in https://anion-gap-checker116.quillnesty.com/posts/how-to-apply-an-anion-gap-calculator-in-renal-failure blood. Laboratory artifact, medication effects, or unusual ion patterns can also play a role.
When the result is unexpectedly low, repeat the analysis if needed and review the entire blood chemistry profile. A low value can be a clue to an underlying disease, but it may also reflect a technical issue or an unrecognized shift in serum electrolytes. The safest approach is to interpret it alongside the rest of the data and the patient’s symptoms.
Correcting Albumin and Why It’s Important
The anion gap after correction accounts for the effect of albumin on the measured result. Since albumin is among the key unmeasured anions, low levels can hide a true acid-base disorder. This is why correcting for albumin is so important when the measured gap seems normal or only mildly abnormal.
In general, a decreased serum albumin means the expected gap should be raised accordingly. The exact adjustment may vary by institution, but the purpose is the same: to avoid missing metabolic acidosis that is being masked by hypoalbuminemia. If the corrected value is elevated, the patient may actually have a high anion gap metabolic acidosis despite a deceptively ordinary initial number.
Working with the adjusted result improves anion gap correction and helps align the lab finding with the patient’s physiology. This step is especially helpful in critically ill patients, those with chronic illness, or anyone whose albumin is known to be low. In other words, correction makes the diagnostic tool more accurate in real-world clinical context.
Frequent Causes and Clinical Background
The most useful assessment is obtained by linking the number with the likely cause. Renal failure can elevate the gap because acids are held back and uremia adds to the buildup of unmeasured materials. Sepsis may trigger lactate production and lead to lactic acidosis. Ketoacidosis may develop in diabetes, alcohol use, or prolonged fasting. These patterns all represent different forms of metabolic disturbance, but they can overlap on a laboratory panel.
Salicylate toxicity and toxic alcohols are especially essential not to miss because they can lead to severe abnormalities and require urgent treatment. The anion gap does not pinpoint the toxin, but it can raise suspicion early. In a patient with altered mental status, unexplained acidosis, or a sudden change in the electrolyte profile, these causes should move high on the list.
Patient setting matters because the same laboratory result can indicate different things in different patients. For example, a modest elevation in a stable outpatient may warrant a different response than a similar value in a critically ill patient with worsening acid-base balance. The calculator is best used as part of a broader diagnostic evaluation, not as a isolated answer.
Detailed Analysis Method
A structured workflow makes anion gap interpretation more consistent and less prone to miss significant findings. Proceed with the electrolyte panel and check the sodium, chloride, and bicarbonate values used in the calculation. Afterward compare the result with the lab’s reference range. From there decide whether the pattern suggests a normal anion gap, a high anion gap metabolic acidosis, or a low anion gap.
Next, assess acid-base status with a blood gas if available. The blood gas aids to confirm whether there is true acidemia or alkalemia and can distinguish mixed disorders. If the anion gap is elevated, evaluate the delta gap to look for additional acid-base processes. This step is especially useful when the bicarbonate drop does not match the degree of gap elevation.
A useful sequence is:
- Check the serum sodium, serum chloride, and serum bicarbonate. Check the reported result from the anion gap calculator. Check for albumin abnormalities and use corrected anion gap interpretation. Assess for clues to lactic acidosis, ketoacidosis, renal failure, or toxin exposure. Calculate the delta gap when mixed disorders are possible. Interpret the result with the patient’s symptoms and overall clinical context.
This structured approach supports better lab interpretation and reduces overreaction to a single laboratory result. It also makes the process easier to repeat when serial labs are collected.
When Further Evaluation Is Needed
More evaluation is needed when the result is far outside the expected range, when there is a sudden change from prior testing, or when the pattern does not fit the clinical picture. Critical values should be treated seriously, especially if the patient has concerning clinical symptoms such as shortness of breath, chest pain, confusion, vomiting, or reduced level of consciousness.
If the result appears not in line with the patient’s condition, a repeat test can assist confirm whether the value is genuine or due to specimen handling, the timing of collection, or analyzer variation. In certain cases, a confirmatory arterial blood gas is required to better define acid-base status. This is especially crucial when there is suspected metabolic acidosis or a mixed disorder that calls for close observation.
Seek prompt reassessment when the anion gap is abnormal and the patient has progressive symptoms, suspected poisoning, signs of shock, or kidney dysfunction. A calculator is a valuable starting point, but it does not substitute for careful medical review, repeat measurement, or broader diagnostic evaluation when the situation is clinically unstable.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used to interpret routine blood chemistry and help identify patterns of metabolic acidosis. It uses the values from a basic metabolic panel or electrolyte panel to estimate whether there are extra unmeasured acids or other abnormalities affecting acid-base balance. It is a useful diagnostic tool for lab interpretation.
What does a high anion gap mean?
A high result often suggests high anion gap metabolic acidosis, which can be caused by lactic acidosis, ketoacidosis, renal failure, uremia, toxic alcohols, or salicylate toxicity. The meaning depends on the patient’s clinical context, symptoms, and other lab findings.
Can low albumin affect the anion gap?
Yes. Albumin is a major unmeasured anion, so hypoalbuminemia can reduce the measured anion gap. That is why corrected anion gap interpretation and albumin correction are significant when the value seems unexpectedly normal or low.
What is the expected anion gap range?
The usual anion gap depends on the lab’s normal range and the method used. Because of laboratory variation, the best approach is to use the range provided alongside the test result. Always read it together with serum electrolytes and the rest of the blood chemistry panel.
When should an abnormal anion gap be evaluated further?
An abnormal result should be investigated further when it is a critical value, when it does not fit the patient’s symptoms, or when there is concern for a serious condition such as acidosis, poisoning, kidney dysfunction, or sepsis. A repeat test, a venous blood gas or arterial blood gas, and review of the delta gap may be needed to clarify the acid-base problem.