What the Anion Gap Calculator Measures
An anion gap calculator is a useful diagnostic tool used to estimate the difference between standard electrolytes in blood. The calculated anion gap helps clinicians assess electrolyte balance and narrow the differential diagnosis of acid-base disorders, especially when evaluating metabolic acidosis.
The calculation relies mainly on sodium, chloride, and bicarbonate. These values come from typical lab values on a chemistry panel, and the result shows the balance between measured ions and unmeasured ions or unmeasured anions in the blood. Because the body must maintain tight acid base balance, a change in the gap can signal a metabolic derangement that requires closer evaluation.
At a basic level, the anion gap is not a direct measurement of acid. Instead, it is a screening estimate that helps detect whether extra acids or other charged particles are present. A rising gap may indicate accumulation of acids, while a low gap can point to albumin changes, lab issues, or unusual cation excess. Used correctly, the calculator supports clinical assessment and more targeted interpretation of a patient’s chemistry profile.
In most settings, the calculator draws from serum sodium, serum chloride, and serum bicarbonate to support rapid bedside reasoning. That makes it especially useful when reviewing a serum chemistry panel in the context of acidemia, alkalemia, or a suspected compensatory response.
Anion Gap Formula and How It Is Calculated
The anion gap formula is commonly written as:
Anion gap = Sodium − (Chloride + Bicarbonate)
This straightforward formula matches the main measured cation, sodium, with the major measured anions, chloride and bicarbonate. Different laboratories may use other conventions, but this is the most familiar version and the one many clinicians use for initial review.
To use an anion gap calculator, start with the chemistry panel. Identify the sodium, chloride, and bicarbonate values. Then work through the equation in order:
- Record the sodium value. Sum the chloride and bicarbonate values together. Take away that sum from sodium. Assess the result with the lab’s reference interval.
For example, if sodium is 140, chloride is 104, and bicarbonate is 24, the gap is 140 − (104 + 24) = 12. That result is often in the normal range, though the exact normal interval depends on the lab.
The calculation is helpful because it turns routine electrolyte data into a clue about hidden acids or shifted ions. In a patient with suspected acid-base disturbance, the gap may reveal whether the problem is associated with excess extra unmeasured anions or with bicarbonate loss and chloride retention. In that sense, the calculator is less about arithmetic and more about clinical pattern recognition.

Typical Anion Gap Range and Meaning
The normal range for anion gap varies by instrument and method, so the most important reference is against the local lab reference range. A value that looks high in one lab may be normal in another. This is why anion gap results should always be read in context rather than in isolation.
A increased anion gap usually points to the presence of extra acids or other unmeasured substances that increase the gap. A decreased anion gap is less common and often is due to hypoalbuminemia, lab variation, or unusual ionic states rather than a primary acid-base disorder.
Assessment depends on the entire biochemical picture. For example, a borderline result in a stable patient may not be meaningful, while the same value in someone with vomiting, altered mental status, or shock may be a critical clue. The calculator is therefore best viewed as part of broader clinical assessment, not a stand-alone answer.
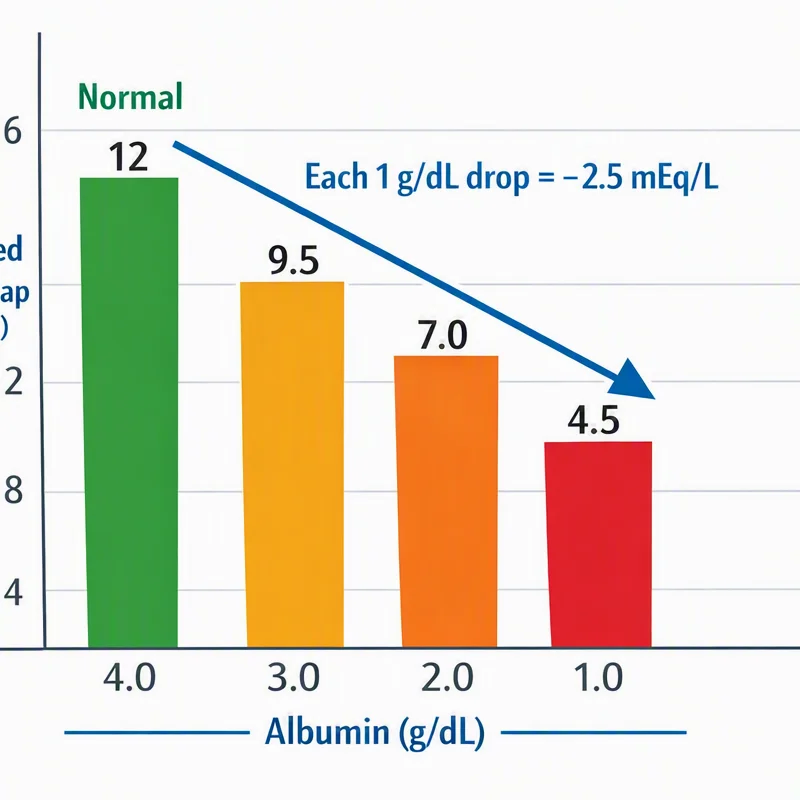
Remember that the anion gap is influenced by the concentration of negatively charged proteins, especially serum albumin. Since albumin contributes substantial negative charge under normal conditions, a low albumin level can make the gap look falsely normal or low. That is one reason the raw number should always be read alongside the broader acid-base picture.
How the Anion Gap Helps Identify Acid-Base Disorders
The anion gap proves most helpful when reviewing acid-base disorders, particularly when the question is whether metabolic acidosis is present and what type it may be. Practically speaking, it helps tell apart acid gain disorders and bicarbonate loss disorders.
In high anion gap metabolic acidosis, the body accumulates acids that are not directly measured on the chemistry panel. These acids raise the gap because bicarbonate declines as it buffers excess hydrogen ions, while chloride may not rise enough to fully compensate.
In normal anion gap metabolic acidosis, bicarbonate is lost and chloride rises in a compensatory pattern. The measured gap can still appear normal even though the patient is clearly acidotic. This is why the anion gap calculator is so useful: it distinguishes different metabolic patterns that can look similar on first inspection.
The gap can also be informative in mixed pictures involving respiratory alkalosis. For example, a patient may hyperventilate and lower carbon dioxide while also developing metabolic acidosis. In that setting, relying on one number can create a false sense of clarity. Careful analysis of pH, bicarbonate, and the anion gap helps detect a mixed disorder.
In general, the calculator supports a stepwise approach to acid base balance. It helps clinicians move from a single abnormal lab result to a more complete interpretation of the underlying physiology.
Elevated high anion gap acidosis causes
A raised gap indicates added acids or acid equivalents that remain in the body. Typical causes are lactic acidosis, ketoacidosis, renal failure, and the intake of toxic alcohols. These conditions all increase unmeasured acid in the blood and alter the biochemical profile from normal.
Lactic acidosis happens when lactate production exceeds clearance, commonly in cases of tissue hypoperfusion, sepsis, severe exertion, or impaired metabolism. Because lactate is an unmeasured anion in routine chemistry, it can elevate the gap significantly.
Ketoacidosis is another leading cause. It may be seen in diabetes, prolonged fasting, heavy alcohol use, or other states of carbohydrate deprivation. Ketone bodies such as beta-hydroxybutyrate and acetoacetate drive the rise in the gap and often accompany symptoms of dehydration, nausea, and altered mental status.
Renal failure can elevate the anion gap because the kidneys are unable to excrete acid effectively. As acids accumulate, bicarbonate falls and unmeasured acids rise. The result is a metabolic pattern that frequently signals advanced disease or acute worsening.
Toxic alcohols such as methanol and ethylene glycol can also produce a high gap. These substances are metabolized into acidic compounds that create significant metabolic derangement. In the right setting, this pattern is a medical emergency and should prompt immediate evaluation.
Even though the anion gap does not identify the exact toxin or acid, it is a powerful clue that guides further testing and treatment. That is why it is often one of the first numbers reviewed in suspected poisoning or unexplained acidemia.
Typical Anion Gap Acidosis with Normal Anion Gap Causes
A normal anion gap does not rule out acidosis. In normal anion gap metabolic acidosis, the key issue is often bicarbonate loss rather than build-up of a new acid. The gap stays stable because chloride rises as bicarbonate falls, preserving the body's charge balance.
Typical causes include diarrhea, renal tubular acidosis, and other forms of bicarbonate loss. This pattern is often called hyperchloremic acidosis because chloride increases as bicarbonate decreases.
Diarrhea can cause marked gastrointestinal bicarbonate depletion, especially when long-lasting or intense. The kidneys may attempt to compensate, but the chemistry panel often shows low bicarbonate and high chloride with a largely normal anion gap.
Renal tubular acidosis refers to impaired renal handling of acid or bicarbonate. Depending on the subtype, the kidneys may fail to acidify urine properly or may waste bicarbonate. Either way, the result can be persistent metabolic acidosis with a normal gap.
Other conditions can resemble this pattern, including specific fluids, chronic kidney conditions, and mixed metabolic states. This is where careful interpretation matters: a normal gap should not stop the evaluation if the patient has a clearly low bicarbonate or a clinical picture consistent with acidosis.
The practical takeaway is simple: if the chemistry panel shows metabolic acidosis but the gap is not elevated, think about bicarbonate depletion, chloride retention, and causes of hyperchloremic acidosis before assuming the problem is mild or resolved.
Accounting for the Anion Gap for Albumin
Because albumin serves as a major negative protein in plasma, low albumin can conceal a true elevation in the anion gap. This is why albumin correction is an integral part of modern interpretation. Without it, a patient with significant acid accumulation may appear to have a normal result.
The corrected anion gap adjusts the measured value to account for hypoalbuminemia. The exact correction factor may differ slightly by formula, but the principle is the same: when albumin is low, restore a portion of the missing negative charge to approximate the true gap more accurately.
This is important because albumin contributes to protein binding and overall charge balance. If albumin falls, the measured gap may narrow even when unmeasured acids are present. In that situation, a seemingly normal anion gap may obscure a clinically important high-gap process.
Albumin correction improves interpretation in patients with liver disease, malnutrition, critical illness, or inflammation, where hypoalbuminemia is common. It is especially useful when evaluating possible lactic acidosis, ketoacidosis, or toxin exposure in a patient whose chemistry panel does not appear striking at first glance.
In practice, the corrected value should be considered alongside pH, bicarbonate, and the rest of the electrolyte profile. The goal is not merely to calculate a number, but to avoid missing a serious acid-base disorder because of altered protein levels.
Frequent Errors and Limitations
Although the anion gap calculator is useful, it has limitations. One of the most common issues is lab error. A hemolyzed sample, transcription problem, or analyzer variation can distort the result. When the number does not align with the clinical picture, repeating the test is often the safest first step.
Another limitation is the presence of unmeasured cations. Substances such as lithium, severe magnesium elevation, or other cation excesses can lower the gap and obscure interpretation. Some medications may also alter acid-base status directly or indirectly, making the chemistry pattern harder to read.
Reading issues frequently occur when doctors focus on the anion gap alone and overlook the full acid–base context. The gap should be considered with pH, bicarbonate, carbon dioxide, and the patient’s general status. Otherwise, a mixed disorder or compensatory response may be undetected.
A further pitfall is forgetting that a “normal” result depends on the specific reference range. One value may be outside the normal range relative to one test and within range in a different one. So every reading should be https://anion-gap-widget797.almoheet-travel.com/can-the-anion-gap-be-used-to-monitor-treatment interpreted using the lab’s own reference interval rather than an presumed universal limit.
Finally, the anion gap doesn’t determine the reason by itself. It is a hint, not a diagnosis. Appropriate use requires connecting the number to the broader context of electrolyte balance, clinical findings, and likely exposures. Together, these factors is what makes the calculator clinically useful.
Anion Gap Calculator FAQ
What is an anion gap calculator used for?
An anion gap calculator is employed to assess acid-base disorders, notably metabolic acidosis. It helps clinicians determine whether the problem is more consistent with a elevated-gap process such as lactic acidosis or ketoacidosis, or a normal anion gap process such as diarrhea or renal tubular acidosis. In that sense, it serves clinical use as a fast triage and interpretation tool.
How do you calculate the anion gap from lab values?
Apply the anion gap formula: sodium subtracts the total of chloride and HCO3. Put simply, anion gap = sodium − (chloride + bicarbonate). This calculation comes directly from a serum chemistry panel and is one of the standard forms of gap calculation in clinical routine.
How does a elevated anion gap mean in acid–base disorders?
A increased anion gap usually means there are more unmeasured anions or unmeasured acids in the blood. With metabolic acidosis, that frequently suggests lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. It is an important clue in acid-base assessment, but it still requires clinical context.
Why should you correct the anion gap for albumin?
You adjust for albumin because reduced albumin can falsely lower the measured gap. With albumin correction, the corrected anion gap better reflects the true acid-base balance, especially in hypoalbuminemia. This avoids missing a clinically important disorder when the raw value looks normal.
What leads to a normal anion gap metabolic acidosis?
Normal anion gap metabolic acidosis is commonly caused by diarrhea, renal tubular acidosis, and other forms of bicarbonate loss. It is often described as hyperchloremic acidosis because chloride increases as bicarbonate falls. If the bicarbonate is low but the gap is not elevated, these causes should be part of the diagnostic workup.