What the Anion Gap Measures
The anion-gap is a calculated value used to aid interpret electrolyte levels and see how the body is maintaining acid-base balance. An Anion Gap Calculator estimates the blood anion gap from routine biochemistry values, usually sodium, chloride, and bicarbonate. This provides a practical tool for fast clinical review of an electrolyte test.

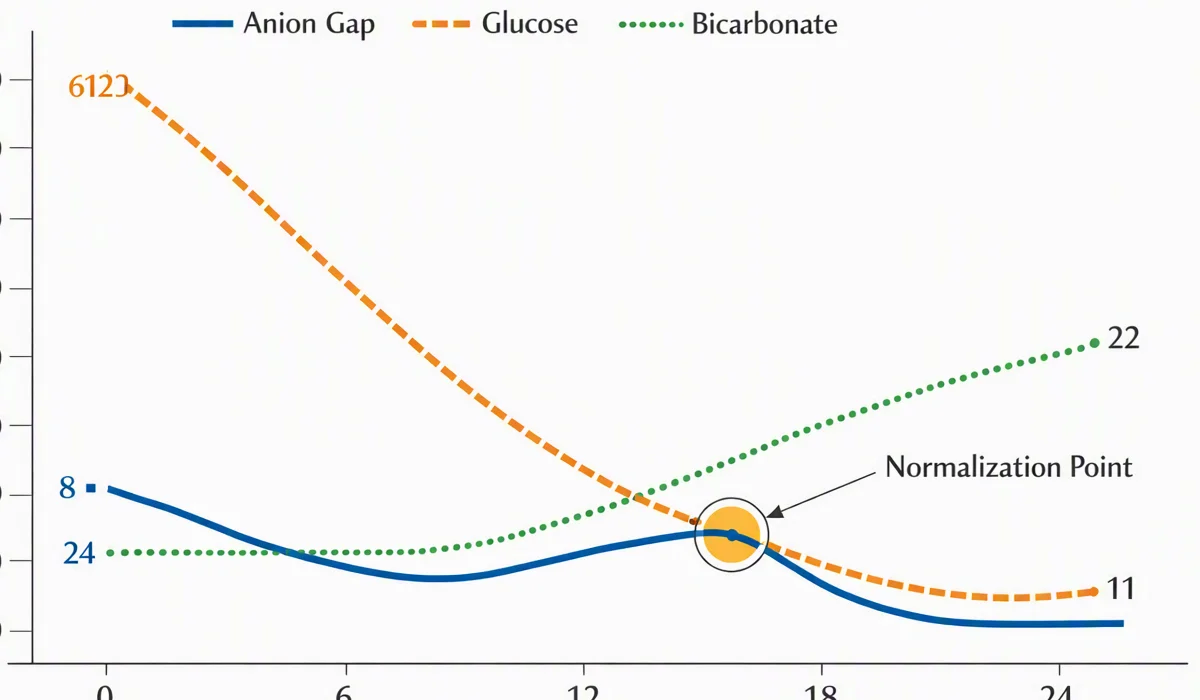
The calculation helps detect whether there may be excess unmeasured anions in the blood. These are substances not directly shown on a standard chemistry report but that still influence the overall charge balance. When the gap is elevated anion gap, it can point toward conditions such as metabolic acidosis. When it is decreased anion gap, it may suggest issues such as low albumin, laboratory problems, or other less common causes.
Because the anion gap is derived from everyday laboratory values, it is widely used as a screening and follow-up measure rather than a standalone diagnosis. It gives context to other findings and can help narrow the differential in an acid-base problem. In short, it is a simple way to calculate anion gap results and connect them to broader physiology.
Using the Anion Gap Calculator
Using an Anion Gap Calculator is simple. You enter the relevant input values from the lab report: serum sodium, serum chloride, and plasma bicarbonate. The tool then uses the anion gap formula and returns the calculator result.
These calculators are created for quick interpretation of routine electrolytes. Some may also let you add albumin for a corrected anion gap, which can be useful when protein levels are abnormal. This matters because albumin is one of the major unmeasured negatively charged substances in blood chemistry.
To use the calculator well:
- Enter the exact numbers shown on the lab report. Check the units match the calculator’s expected format. See whether the tool uses a standard or albumin-adjusted calculation. Check the normal range shown by the calculator or your lab source.
The result should be interpreted in context. A single number may look normal, but if the patient has symptoms or other abnormal lab values, the overall picture may still point to a clinically important problem. Likewise, a mildly abnormal result may be not as concerning if it fits the expected picture of the patient’s condition.
Anion Gap Formula and Interpretation
The usual anion gap formula can be written as Na minus Cl minus HCO3. Put differently, it means subtracting chloride and bicarbonate from sodium. This simple formula estimates the difference between commonly measured positive and negative ions in the blood.
The usual logic is that sodium is the main measured cation, while chloride and bicarbonate are the main measured anions included in the calculation. It represents the charge contributed by unmeasured ions. A normal or normal anion gap points to a relatively balanced pattern of measured and unmeasured ions, while a shift in either direction can reveal a hidden disturbance.
An important refinement is albumin correction. Albumin plays a major role in the anion gap because it carries negative charge. When albumin is low, the measured gap may appear falsely low. A corrected anion gap can therefore more accurately represent true physiology in certain patients.
An elevated anion gap often indicates increased unmeasured acids in the blood, which is a major clue in metabolic acidosis. A low anion gap is rarer, but it can be clinically meaningful when it reflects hypoalbuminemia, excess positively charged proteins, or technical error.
Think of the anion gap as a clue, not a diagnosis. It helps identify whether the blood chemistry pattern suggests hidden acids, protein shifts, or a measurement problem.
Common Causes of a elevated anion gap
A elevated anion gap usually indicates there may be extra acids or unmeasured anions in the bloodstream. This pattern is especially important in metabolic acidosis, where acid buildup lowers bicarbonate and changes the overall electrolyte picture.
Typical causes include:
- Lactic acidosis, where lactate rises because of poor oxygen delivery, shock, sepsis, or other stress states. Ketoacidosis, including diabetic ketoacidosis, alcoholic ketoacidosis, or starvation-related ketosis. Renal failure, where the kidneys cannot clear acids effectively. Toxic ingestion, such as exposure to substances that generate acid metabolites or interfere with normal metabolism.
These causes are important because they point to very different treatments. For example, lactic acidosis may require urgent stabilization and correction of the underlying cause, while ketoacidosis requires insulin, fluids, and careful electrolyte management. In renal failure, impaired acid elimination and electrolyte handling often drive the abnormal result. With toxic ingestion, the pattern may be a critical diagnostic clue.
The calculator result alone does not tell you which cause is present. It only highlights that there may be extra unmeasured anions, prompting further review of the patient’s symptoms, lab results, and acid-base status.

Frequent Causes of a Low Anion Gap
A decreased anion gap is uncommon than a high one, but it can still be important. The most frequent explanation is hypoalbuminemia, since low albumin eliminates a major source https://jsbin.com/nuhaficagu of negative charge from the measured system. In many cases, this is why albumin correction is so important.
Additional common causes are:
- Lab error, which is always worth checking if the result does not fit the clinical picture. Paraproteinemia, where abnormal proteins create unusual positive charge patterns. Hyperchloremia, which can decrease the calculated gap by shifting the relationship between sodium, chloride, and bicarbonate.
A low gap may also be seen when the measurement technique or specimen handling influences the reported values. Because of that, a repeat panel is sometimes needed before concluding that the result reflects a true disorder. Reviewing the reference range and the patient’s overall status helps determine whether the low result is significant.
When hypoalbuminemia is present, the apparent low gap may not indicate a true acid-base problem. Instead, the value may simply reflect reduced albumin concentration. That is why the serum anion gap should always be interpreted with the protein level in mind.
Constraints of the Calculator
An Anion Gap Calculator is practical, but it has specific limitations. First, the result depends on the accuracy of the entered lab values. If the sodium, chloride, or bicarbonate measurement is incorrect, the calculated gap will also be incorrect. Even small shifts in the input values can change the result.
Next, calculators may use slightly different reference range cutoffs depending on the laboratory or method. That means a value considered normal in one setting may be borderline in another. Some calculators also use different assumptions about whether potassium is included, which can affect the interpretation slightly.
Third, albumin can significantly affect the interpretation. A calculator that does not include albumin may miss a true abnormality or make a low value look more worrisome than it is. A corrected anion gap can improve interpretation, but it still does not substitute for full clinical assessment.
Likewise, the anion gap is only one piece of the puzzle. It does not replace an arterial blood gas when a detailed evaluation of pH, carbon dioxide, and compensation is needed. It also does not identify the specific cause of an abnormality. It provides diagnostic support, not a final diagnosis.
In the end, the calculator must be interpreted in clinical context. Symptoms, medication history, kidney function, nutrition status, and other chemistry results all influence what the number means. A result can be unremarkable and still miss a developing problem, or it can be abnormal without indicating an emergency.
When to Seek Medical Interpretation
If the calculator shows a notable shift, medical review is essential. An abnormal Anion Gap Calculator can signal an acid-base disorder, especially if it is accompanied by low bicarbonate, abnormal pH, or worrisome symptoms. This is most true when the pattern suggests a metabolic acidosis.
Clinical interpretation is also important when there is a more general electrolyte disturbance. Because the result depends on the relationship among sodium, chloride, and bicarbonate, other disturbances in electrolyte levels can change the meaning of the number. A value that seems somewhat abnormal may become more concerning if the person is dehydrated, critically ill, or has kidney dysfunction.
You should seek a medical professional for interpretation when:
- The result is clearly above or below the expected range. There are symptoms such as disorientation, fast breathing, vomiting, weakness, or severe fatigue. The patient has diabetes, kidney disease, suspected poisoning, or another significant illness. The calculator suggests a increased anion gap or decreased anion gap that does not match the clinical picture.
The blood anion gap is most useful when viewed as part of a larger assessment. In practice, it often points to the next step: repeat testing, albumin adjustment, blood gas analysis, or investigation for a specific cause of acidosis or protein abnormality.
Frequently Asked Questions
What is a normal anion gap?
The anion gap normal range changes by laboratory method and the tool used. Many references view a typical result to sit within a relatively limited expected range, but the precise cutoff should be taken from the lab report or the calculator used. The most important point is to match the result with the range attached to the specific laboratory values being interpreted.
How do you calculate the serum anion gap?
You determine the anion gap in serum using the gap formula: Na - Cl - HCO3. Practically, you input the measured sodium, Cl, and bicarbonate into an Anion Gap Calculator. The calculator then gives the gap as a quick summary of the balance between measured and unmeasured ions.
What does a high anion gap indicate?
A raised anion gap usually points to excess unmeasured anions from an acid load, which often suggests acid-base acidosis. Common causes include an elevated lactate state, ketoacidosis, renal insufficiency, and toxin exposure. The result is a clue that should be interpreted alongside symptoms, kidney function, and other chemistry findings.
Should the anion gap be corrected for albumin?
Yes, albumin-based correction can be very helpful when albumin is low. Since albumin is a major negatively charged protein, low levels can make the anion gap appear falsely low. A corrected anion gap may give a more accurate picture of acid-base status, especially when there is suspected acidosis or unexplained abnormalities in the electrolyte panel.
How reliable is an Anion Gap Calculator?
An Anion Gap Calculator is generally reliable for the arithmetic calculation, but its usefulness depends on the quality of the input and the broader medical interpretation. It can accurately compute the number from laboratory values, but it cannot determine the cause of an abnormal result on its own. Accuracy also depends on whether the calculator accounts for serum albumin, uses the correct expected range, and reflects the same method as the lab report. For that reason, it is best used for diagnostic support, not as a substitute for medical evaluation.